Validated is not the same as FDA cleared
Most people assume a monitor sold in a US pharmacy has had its accuracy checked. It may not have. Home blood pressure monitors reach the market through the FDA's 510(k) clearance route, and a 2019 review making the case for the US validation listing sets out what that does and does not require. Manufacturers need only show a new device is approximately as safe and effective as similar devices already on the market. The process does not contain explicit requirements to demonstrate accuracy, does not mandate a validation protocol, and does not require an independent, peer-reviewed validation study; internally generated data can be submitted, and they are not readily available to the public.
Validation is a separate, specific test. The 2025 AHA/ACC blood pressure guideline explains why it matters for the automatic monitors almost everyone uses at home: these oscillometric devices estimate systolic and diastolic pressure with proprietary manufacturer algorithms, so only devices validated with a rigorous standardized protocol against a reference standard are recommended. For home monitoring specifically, the guideline says it is important to ensure the device has been validated with a rigorous, standardized protocol and that the appropriate size cuff is used.
What a validation study actually tests
In a validation study, the monitor's readings are compared with simultaneous measurements taken by trained observers with a reference instrument, across a set number of people with a spread of blood pressures and arm sizes. The benchmark is the ISO 81060-2 standard. In 2018, the US Association for the Advancement of Medical Instrumentation (AAMI), the European Society of Hypertension (ESH) and the International Organization for Standardization (ISO) published the agreed key aspects of a single universal validation protocol, and the 2019 review behind the US listing summarizes the ISO 81060-2:2013 pass criteria. The standard has been revised since; we did not open the current edition, so the criteria below are the 2013 edition's as these two papers state them, not necessarily the current text.
| Requirement | What it says |
|---|---|
| Number of people | At least 85 in a general-population study |
| Criterion 1 (ISO 81060-2:2013) | Mean difference between device and reference of 5 mmHg or less, with a standard deviation of 8 mmHg or less, for systolic and diastolic pressure |
| Criterion 2 (ISO 81060-2:2013) | Analyzed as 85 paired results, one per person, the standard deviation of the difference must be below a threshold of 4.79 to 6.95 mmHg, which varies with the mean difference observed |
| Tolerable error the universal protocol is built around | An error of 10 mmHg or less, with an estimated probability of at least 85%, using each person's average of three readings against the reference |
| Special populations | Groups such as children and pregnancy need their own study; once a general-population study has passed, a minimum of 35 people (45 for pregnancy) is accepted |
The statement is candid about that 10 mmHg figure: it does not reflect an acceptable level of inaccuracy, but allows for the variability of the method itself. A validated device is one shown to be accurate on average across a tested group. It is not a promise about every arm.
How the US Validated Device Listing works
The US Blood Pressure Validated Device Listing, at validatebp.org, is run by the American Medical Association, not by the American Heart Association, although the AHA/ACC guideline cites it as a carefully vetted list of validated devices available in the United States. According to the AMA, hypertension experts began meeting in 2015 to set criteria; the AMA then funded NORC at the University of Chicago to design and manage an independent review. An all-volunteer Independent Review Committee decides whether a device meets the criteria. NORC distributes each manufacturer's submission to at least two committee members, and committee members are cleared by the AMA for expertise and conflicts of interest.
The 2019 review that reported the listing's proposed entry criteria required a validation study under one of the 85-subject protocols, from the ANSI/AAMI/ISO family or the revised British Hypertension Society protocol, documented by a peer-reviewed publication or by independent third-party testing. The shorter 33-person European protocol alone was not enough. In 2019 that was a stricter bar than the Hypertension Canada and British and Irish Hypertension Society listings, which accepted it.
Using it is simple. On our reading, validation belongs to the specific model that was tested, so search the listing for the exact model number on the box rather than the brand. Check that the monitor's cuff covers your arm size. If you are pregnant, the guideline advises a monitor specifically validated for accuracy in pregnancy.
How often store-bought monitors are unvalidated
Often. A study published in JAMA in 2023 tracked the 100 best-selling blood pressure devices on Amazon in 10 countries every 8 weeks from February 2020 to January 2021, checking each against validation listings, including the US listing for US products. In the United States, a median of 84% of upper-arm monitors and 100% of wrist monitors on the list were not validated. In every country, unvalidated upper-arm and wrist monitors cost less than validated ones, and across all 10 countries unvalidated upper-arm monitors received the same median consumer rating as validated ones, 4.5 out of 5 stars. Reviews cannot tell you whether a monitor is accurate.
Sponsored option
Vetted Aug 19, 2026Affiliate link, we may earn a commission at no extra cost to you.

Everlywell Our score 4.0/5
At-home lab tests
Pricing as of Aug 19, 2026
HbA1c $49; cholesterol and lipids $49; heart health panel $99
The cuff and the arm matter as much as the device
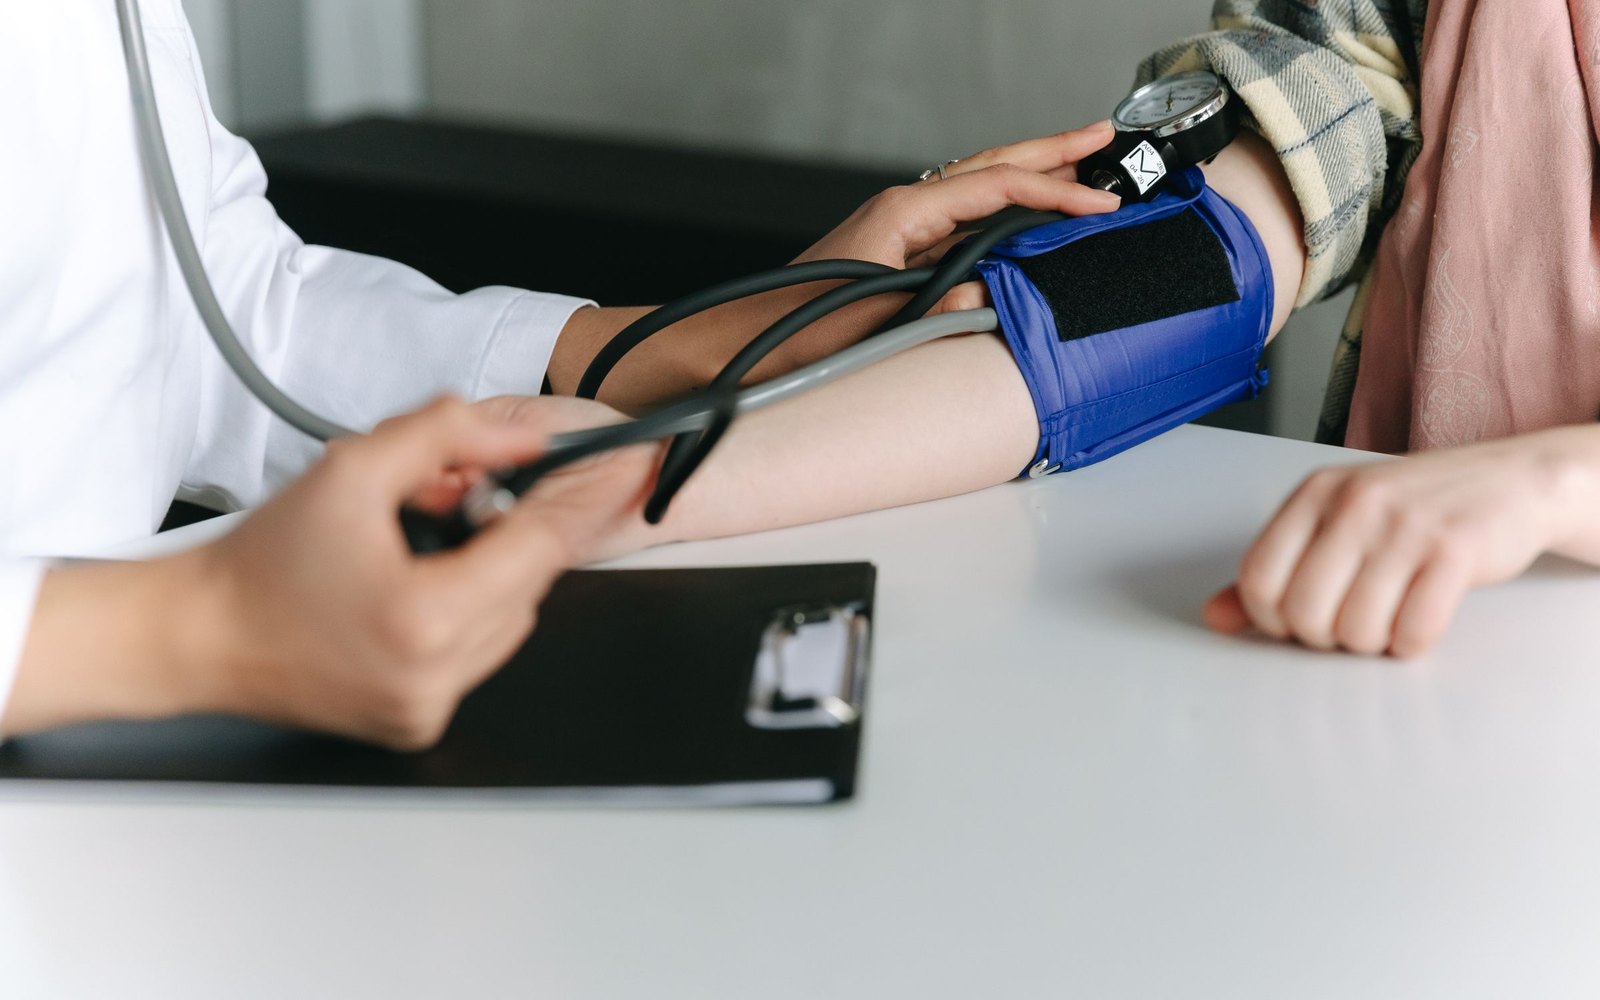
Cuff size. The AHA's scientific statement on measurement says the cuff bladder should be 75% to 100% of the arm's circumference in length, measured at the midpoint of the upper arm. In the Cuff(SZ) randomized crossover trial of 195 adults in Baltimore, using a regular adult cuff on people who needed a different size gave readings that were wrong in a predictable direction: systolic pressure read 3.6 mmHg low in people who needed a small cuff, 4.8 mmHg high in people who needed a large cuff, and 19.5 mmHg high in people who needed an extra-large one. Measure your upper arm before you buy and choose a model whose cuff covers it.
Upper arm, not wrist. The AHA statement recommends a validated upper-arm cuff device for home monitoring. It notes that wrist monitors read accurately only if the sensor sits directly over the radial artery and the wrist is held at heart level, two conditions that are easy to miss at home.
Smartwatches and cuffless devices. The 2025 guideline reviewed cuffless technology and concluded that its limitations must be overcome before cuffless devices can be recommended for clinical use, noting that few validation protocols exist for them. Our guide to blood pressure ranges covers what that means for the numbers your watch shows.
Irregular heart rhythm. The guideline notes that oscillometric devices have typically been validated in people in normal sinus rhythm, and that validation evidence in atrial fibrillation is limited. If you have atrial fibrillation, ask whether your readings should be checked against a manual measurement.
Check your own monitor against the office
A device can pass validation and still read differently on you. The AHA statement's guidance for home monitoring tells clinicians to have patients bring the device and their readings to healthcare visits. The 2019 listing review describes how a clinic can compare a home device with a manual reading on the arm with the higher pressure, and its authors write that, in their experience, five comparisons is optimal. If your monitor consistently disagrees, one fix the review suggests is a device from a different manufacturer that performs better on you.
How to take a reading the guideline would accept
The AHA statement's home monitoring guidance comes down to a short routine. Empty your bladder. Sit with your back supported, feet flat and legs uncrossed, and rest quietly for at least 5 minutes without talking or texting. Put the cuff on bare skin, just above the bend of the elbow, with the arm supported on a table. Take 2 readings at least 1 minute apart in the morning before blood pressure medicine, and 2 more in the evening before bed. The preferred monitoring period is at least 7 days, or 28 readings; 3 days, or 12 readings, may be enough. Average them all.
Home numbers do not translate one to one at every level. The guideline's table pairs a home average of 130/80 with an office reading of 130/80, but a home average of 135/85 with an office 140/90, and warns these pairings come mainly from European, Australian and Asian populations. Our guide to whether walking lowers blood pressure covers the size of the drop the trials found and suggests bringing two weeks of home readings to your next review rather than a single number.
What to do next
Check your monitor's model number against the listing, measure your arm, and take a week of readings the way the guideline describes. Then compare the average with the categories on our blood pressure reference page, which carries each threshold with its source and date. Our hypertension screening page sets out who should be screened and how often, and your personal screening plan puts it alongside the other checks due at your age. Bring the monitor and the log to your next appointment.
Frequently asked questions
Does FDA clearance mean a blood pressure monitor is accurate?
Not on its own. FDA 510(k) clearance requires a manufacturer to show the device is substantially equivalent to devices already sold, and it does not mandate an independent validation study or a specific accuracy protocol. Look the model up on the US Validated Device Listing instead.
Is the validated device list run by the American Heart Association?
No. The US Blood Pressure Validated Device Listing is run by the American Medical Association, with an independent review committee managed through NORC at the University of Chicago. The 2025 AHA/ACC guideline refers readers to it.
Are wrist blood pressure monitors accurate?
Some have passed validation, but the AHA recommends an upper-arm cuff for home use because wrist devices read correctly only with the sensor over the artery and the wrist at heart level. On US Amazon best-seller lists in 2020 to 2021, every wrist monitor was unvalidated.
How do I know my cuff is the right size?
Measure around the middle of your upper arm. The AHA statement says the cuff bladder should be 75% to 100% of that circumference in length, so check the arm range given for the monitor's cuff before you buy. A cuff that is too small reads high: in one trial, a regular cuff read 19.5 mmHg systolic high on average in people who needed an extra-large one.
How often should I check my monitor's accuracy?
The AHA statement's guidance is to bring the device and your readings to healthcare visits, where a clinician can compare it with an office measurement. The 2019 listing review's authors found five side-by-side comparisons optimal in their experience.