Two different measurements of the same traffic
Think of atherogenic lipoproteins as delivery trucks and cholesterol as the cargo. LDL cholesterol weighs the cargo. ApoB counts the trucks, because each LDL, VLDL, IDL and Lp(a) particle carries exactly one apolipoprotein B molecule. Risk tracks with how many trucks are on the road: particles, not cargo, are what cross into the artery wall and start plaque.
When the two numbers disagree
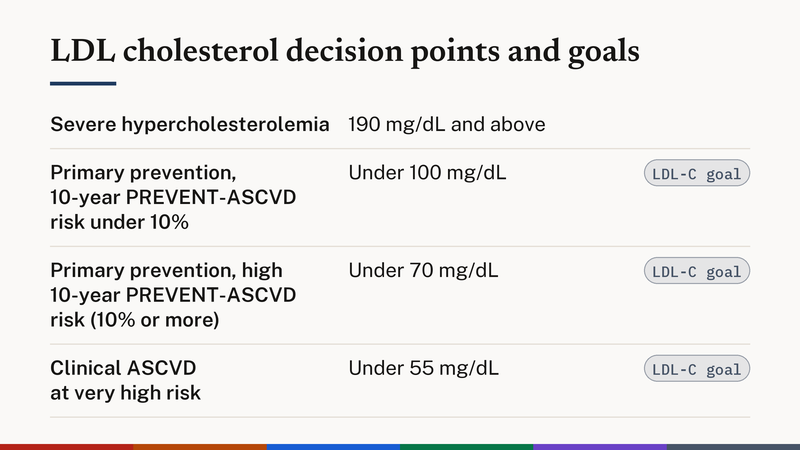
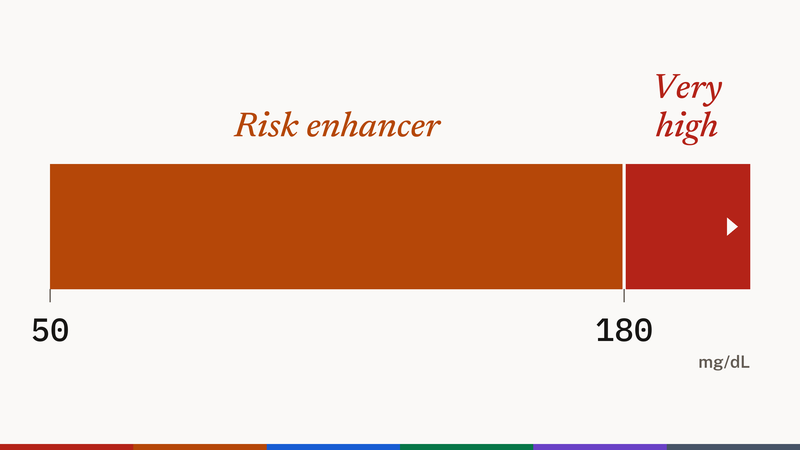
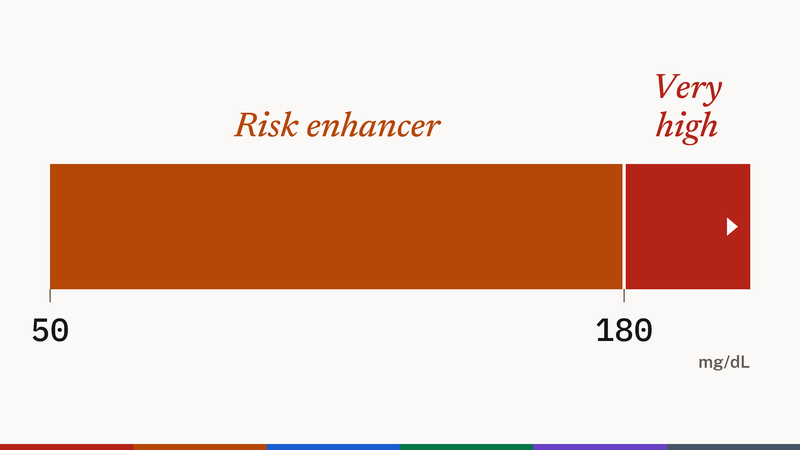
In many adults the two move together and either works. The split happens when particles run small and cholesterol-poor, which is the signature of high triglycerides, insulin resistance, type 2 diabetes and abdominal weight: LDL-C reads normal while the particle count, and the risk, runs high. That discordance is why guideline bodies added ApoB as a tie-breaker. The 2026 ACC/AHA dyslipidemia guideline lists ApoB of 120 mg/dL or higher among its risk enhancers, in one row with an LDL-C persistently 160 to 189 mg/dL or a non-HDL-C of 190 to 219, and the AHA's release on the guideline says ApoB may be used to assess residual risk and guide treatment in people with cardiovascular-kidney-metabolic syndrome, type 2 diabetes, high triglycerides or known cardiovascular disease who have reached their LDL-C and non-HDL-C goals.
The thresholds, in one place
In 2024 the National Lipid Association wrote that "Specific apoB thresholds have not been suggested in U.S. guidelines and recommendations". That changed with the 2026 ACC/AHA dyslipidemia guideline, which the NLA co-authored and endorsed. Its goal figure sets ApoB goals of under 90 mg/dL at a 10-year PREVENT-ASCVD risk under 10% with triglycerides of 150 to 499, or with diabetes without risk factors; under 70 at a risk of 10% or more with those triglycerides, or with diabetes and risk factors; and under 55 for clinical ASCVD at very high risk. Its treatment algorithms for diabetes, high triglycerides and clinical ASCVD label the ApoB goals optional. For comparison, the median ApoB in untreated US adults (NHANES 2005 to 2016, per the NLA) is 90 mg/dL. Two one-page corrections to the guideline were published on June 22 and September 8, 2026, and we could not read them, so the numbers here are as printed in ACC's reproduction of its tables and figures, read October 19, 2026. Our ApoB reference page keeps the full table with sources and dates.
What to actually do
If your triglycerides run above about 150 mg/dL, your A1C sits in the prediabetes range, or your LDL-C has always looked "fine" despite a strong family history, one ApoB test tells you whether the reassuring cholesterol number was telling the truth. The National Lipid Association's 2024 consensus says ApoB changes minimally between fasting and non-fasting samples, and that the test is cheap for a laboratory to run, but it also reports frequent insurance denials and prior-authorization requirements, so ask about coverage before the draw. Pair it once with Lp(a), the inherited particle a standard panel also misses. Everything that lowers LDL-C (statins, ezetimibe, diet built around lower saturated fat and more fiber) lowers ApoB too; the point of measuring is to find the risk, not to change the treatment toolbox.
Frequently asked questions
Should I test ApoB instead of a cholesterol panel?
In addition to, not instead of. The standard panel still carries HDL and triglycerides, which drive the interpretation. ApoB adds the particle count, and once you know your discordance pattern you do not need it at every draw.
What is a good ApoB number?
Context sets the target. The 2026 ACC/AHA guideline sets ApoB goals of under 90 mg/dL at a 10-year PREVENT-ASCVD risk under 10% with triglycerides of 150 to 499, or with diabetes without risk factors; under 70 at a risk of 10% or more with those triglycerides, or with diabetes and risk factors; and under 55 for clinical ASCVD at very high risk. Its treatment algorithms for diabetes, high triglycerides and clinical ASCVD label these ApoB goals optional. The US median of 90 mg/dL in untreated adults is a population statistic, not a goal.
Do I need to fast for ApoB?
ApoB itself barely moves with a meal: the National Lipid Association's 2024 consensus reports minimal change between fasting and non-fasting samples. The same paper notes that the Friedewald formula many labs used to calculate LDL assumes a fasting sample. If another test in the same draw needs a fast, follow that instruction.