The yearly core
Three checks do most of the work. Blood glucose or A1C: the USPSTF recommends screening adults 35 to 70 with overweight or obesity for prediabetes and type 2 diabetes, repeating about every three years while normal, so "yearly" only once something is borderline. A lipid panel (LDL, HDL, triglycerides): from 40 to 75 the USPSTF ties statin decisions to 10-year risk, and the panel is the input. And blood pressure, which is not a blood test but decides more than most of them: the USPSTF suggests yearly screening from 40 and for adults at increased risk, and every 3 to 5 years for adults 18 to 39 not at increased risk with a prior normal reading.
The numbers that ride along
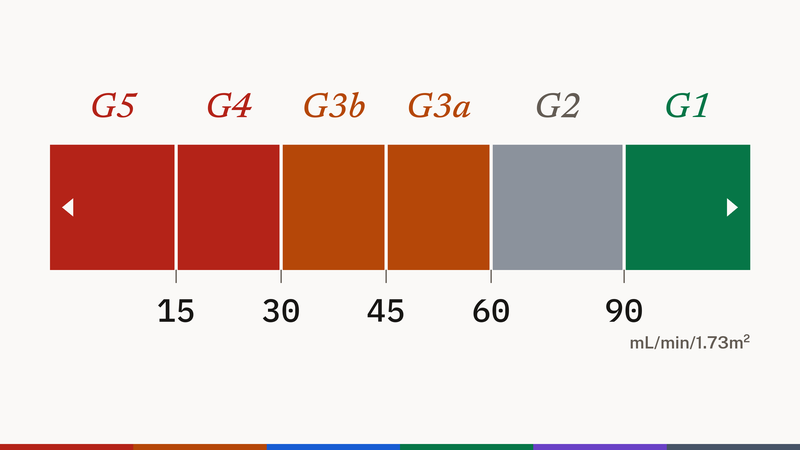
A basic metabolic panel and liver enzymes usually come bundled, and two of those numbers deserve reading rather than skimming. eGFR: below 60 for more than three months defines chronic kidney disease (KDIGO), and 60 to 89 without urine albumin is not disease, it is often normal aging. ALT: the ACG puts the truly healthy upper limit at 33 U/L for men and 25 for women, lower than many lab reports print, and the usual explanation for a creeping ALT is fatty liver that tracks with the glucose and triglyceride numbers above.
Worth doing once, not yearly
Two lipid add-ons carry lifetime information. ApoB counts atherogenic particles and exposes risk hiding behind a normal LDL, most often when triglycerides run high. Lp(a) is more than 90% genetically determined, according to the European Atherosclerosis Society's 2022 consensus, which recommends measuring it at least once in adults. Neither needs an annual slot; both change what "borderline" means for you.
What to skip by default
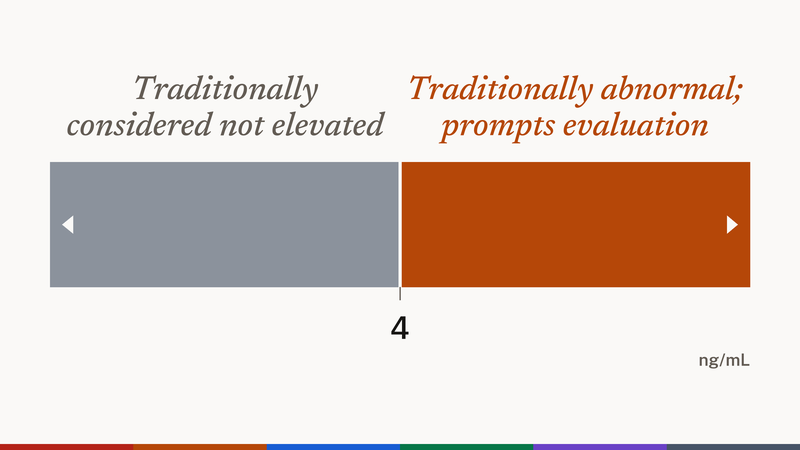
Routine vitamin D testing: the Endocrine Society's 2024 guideline found no trial evidence supporting 25(OH)D screening in the general population and suggests against routine testing without an indication. Ferritin is a targeted test, excellent when fatigue, heavy periods or anemia raise the iron question, not a default. Testosterone, thyroid (TSH) and PSA are symptom- and decision-driven tests with their own pages. The pattern: screen what has a screening rule, test what has a question.
Where to get them
Any primary-care visit covers the core, and results come with someone obliged to act on them. At-home panels can fill gaps between visits for specific numbers (A1C, lipids); treat them as screening, and bring anything abnormal to a clinician. Our Everlywell review sets out what one at-home service charges per test, how its samples are processed and reviewed, and where it does not sell. Our personal screening plan lists the screenings that apply at your age and sex, blood tests included.
Frequently asked questions
How often should I get a full blood panel?
There is no guideline for an annual "full panel" in healthy adults. The screening rules are test-specific: glucose about every 3 years when normal (USPSTF), lipids feeding the age 40 to 75 statin discussion, blood pressure yearly from 40, or every 3 to 5 years at 18 to 39 with a prior normal reading and no added risk (USPSTF). Yearly everything is a habit, not a recommendation, though it is a mostly harmless one.
Do I need to fast before annual blood work?
It depends on the test, so ask what is being drawn. A fasting glucose needs a fast by definition: NHLBI describes the reading after 8 to 12 hours without eating. A1C does not require fasting, per the ADA. For a lipid panel, NHLBI says your provider may ask you to fast for 8 to 12 hours. For ApoB, the National Lipid Association's 2024 consensus reports minimal change between fasting and non-fasting samples.
Are at-home blood test kits accurate?
Kits that mail a sample to a CLIA-certified laboratory are running real assays; the finger-prick collection adds some variability. They are reasonable for screening numbers like A1C and lipids, and no substitute for confirmation when a result would change treatment.